Physics › Medical physics › Radionuclide imaging and the gamma camera
Radionuclide imaging and the gamma camera
A medical tracer is a gamma-emitting radionuclide bound to a molecule the body uses, and a gamma camera maps where the emission comes from. Its collimator selects photon direction, its scintillator converts each photon to light, and photomultiplier tubes place the flash. Physical and biological half-lives combine as reciprocals to give the effective half-life.
Choose your exam board to show the notes and questions relevant to your specification. You can change this setting at any time, and content for other boards remains available.
Radionuclide imaging and PET, part 1 of 2. Part 2 is PET scanning and radiotherapy.
Builds on Half-life and nuclear instability and The physics of diagnostic X-rays.
IN THIS TOPIC
- Explain what a medical tracer is, and why its half-life and emission type must be chosen carefully.
- Distinguish physical, biological and effective half-life, and combine them with 1/T_E = 1/T_P + 1/T_B.
- Describe how emitted gamma rays are used to build an image of where the tracer went.
COMMON MISCONCEPTION
The effective half-life of a tracer is the average of its physical and biological half-lives.
Effective half-life is not an average: the two removals run at once, so the rates add, 1/TE = 1/TP + 1/TB, and TE comes out shorter than either half-life alone, never between them.
Tracers and radionuclide imaging
A tracer is a radioactive nuclide chemically attached to a molecule the body uses, perhaps a glucose analogue or a bone-seeking compound, depending on the question being asked. Injected or swallowed, the molecule goes where the biology sends it, and the nuclide radiates from wherever it accumulates. Detecting that radiation maps function, meaning which tissue is taking up the molecule, which is inflamed, and which has stopped working. An X-ray shows what the body looks like. A tracer shows what it is doing.
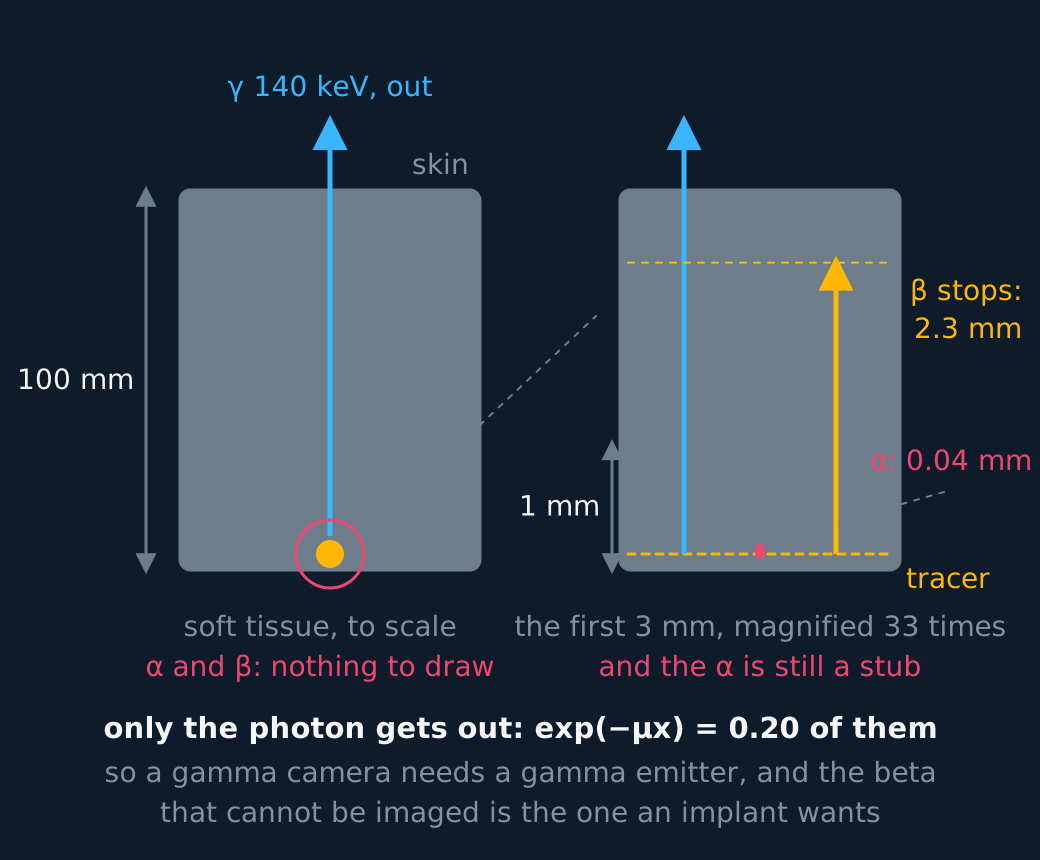
The nuclide must be chosen with care, on two counts. What reaches the detector has to be photons, since charged particles do not get out. For a gamma camera that means a gamma emitter. An alpha emitter is stopped within a fraction of a millimetre of tissue and a beta-minus emitter within a few millimetres, so almost nothing reaches an external detector; both deposit their energy in the patient and are useless as the directly detected radiation of a conventional external image. PET uses that rule rather than breaking it, as the next lesson shows, but for the gamma camera it stands as written.
Describe the drawing
One hundred millimetres of soft tissue with a tracer at the bottom of it, drawn to a single scale in millimetres. The 140 keV gamma photon crosses the whole depth and leaves through the skin, and the exponential law returns about a fifth of the photons surviving. The 5.5 MeV alpha and the 600 keV beta are not drawn at all on that scale, because their ranges of 0.04 mm and 2.3 mm are a fraction of one drawn unit, so a second panel magnifies the first three millimetres above the tracer more than thirty times: only there does the beta become a real arrow, and even there the alpha is a stub. Only photons get out of a patient, which is why a gamma camera has to be given a gamma emitter, and why a beta emitter is useless for imaging and ideal for an implant.
The half-life must suit the job too, long enough to prepare and image, short enough that the patient is not irradiated for weeks. The standard choice is technetium-99m, half-life six hours, a near-pure gamma emitter drawn fresh from a generator as it is needed. Hospitals keep a generator of its parent, molybdenum-99, and elute the technetium as it forms, typically around once a day.
Six hours does not suit every question, and the standard alternative when the biology takes days is indium-111. It decays by electron capture with a half-life of 2.8 days, emitting gamma photons at 171 keV and 245 keV that a gamma camera reads comfortably. Its usual job is labelling a sample of the patient's own white blood cells, which are then returned to the bloodstream and gather wherever there is infection, so a picture taken a day or two later finds an abscess that no shadow image would show. The longer half-life is what makes that possible, and the drawback is that the patient is exposed for longer.
Three half-lives, one that matters
Activity inside a patient falls for two independent reasons, and the specification wants both named and then combined. The physical half-life TP is the ordinary nuclear one, the time for half the nuclei to decay, and nothing a body does can change it. The biological half-life TB is the time for the body to clear half the tracer, by the kidneys, the gut or the breath, and it depends entirely on the chemistry the nuclide is riding on rather than on the nuclide itself.
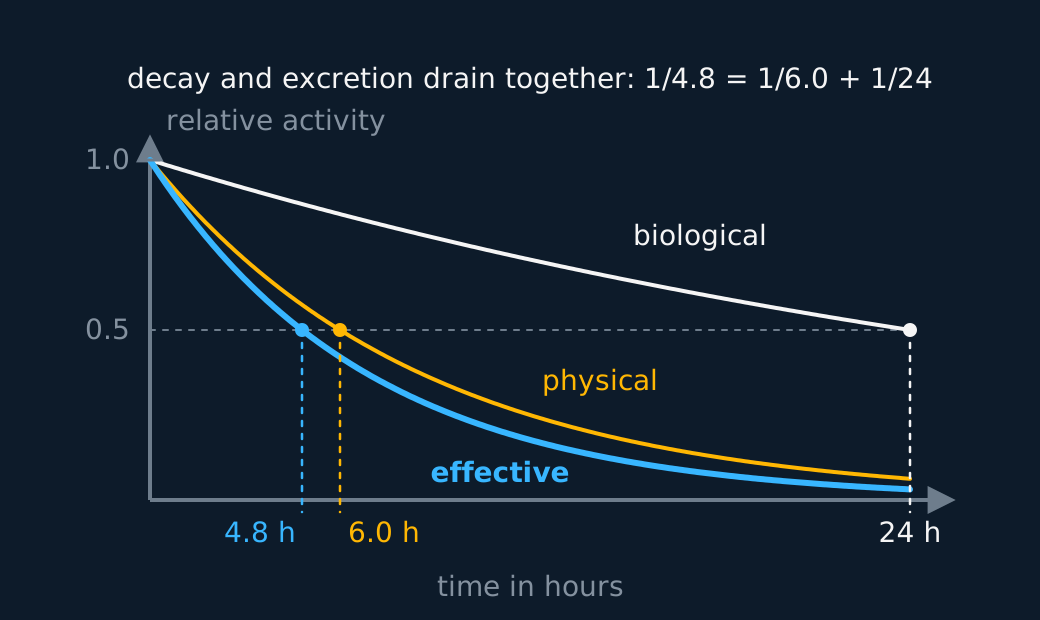
Both drain the same store, and both drain a fixed fraction of what is left per unit time, so the fractional rates simply add. Write each rate as one over its half-life and the result is the effective half-life:
and because rates add, TE always comes out shorter than either of the two half-lives that made it. That is the number a dose calculation needs, since it describes how long the activity actually stays in the patient, and it is the number a scan has to be timed against.
Describe the drawing
Three computed decay curves of relative activity against time in hours for one technetium-99m dose, all starting together at full activity. The white biological curve, excretion alone, halves every 24 hours and falls slowest; the amber physical curve, decay alone, halves every 6 hours; and the bold cyan effective curve, the two drains running together, halves every 4.8 hours and lies below both of the others at every moment. A dashed drop-line in each curve's colour marks where it crosses half activity, at 4.8, 6.0 and 24 hours, and the caption records that the rates add: 1/4.8 = 1/6.0 + 1/24.
WORKED EXAMPLE
How long does the tracer really last?
Technetium-99m has a physical half-life of 6.0 hours. Bound to a compound the kidneys clear with a biological half-life of 24 hours, what is its effective half-life in the patient?
1/TE = 1/6.0 + 1/24 = 0.1667 + 0.0417 = 0.2083 h−1.
TE = 1/0.2083 = 4.8 hours.
Shorter than the six hours of the physics alone, as it must be, because excretion is removing tracer while the nuclide decays. Add the reciprocals rather than averaging the half-lives: the average of 6.0 and 24 hours is 15 hours, longer than the 6.0 hour physical half-life, whereas an effective half-life must come out shorter than both of the half-lives that produced it.
Catching the gammas
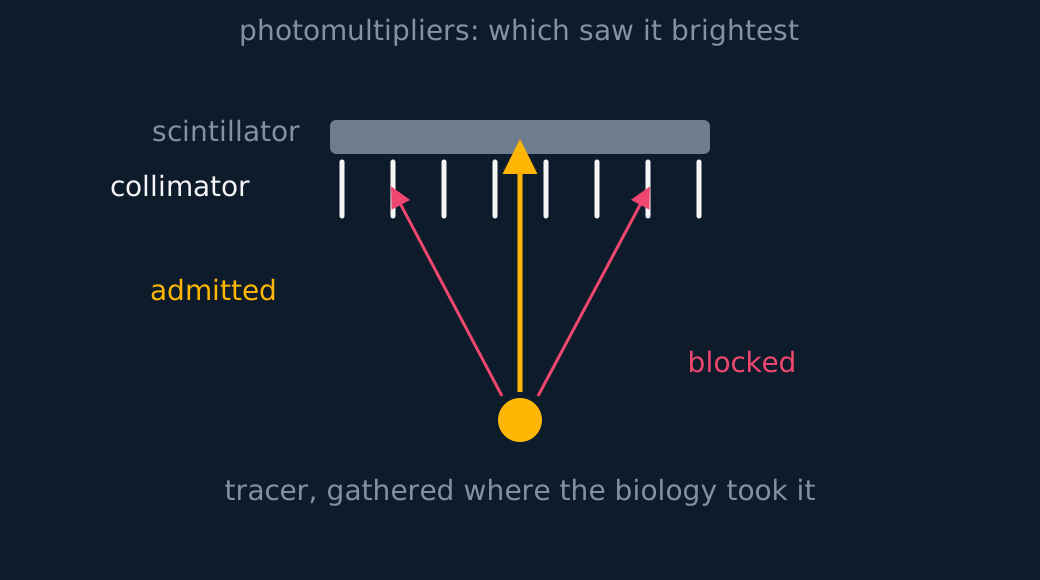
A gamma camera collects the emitted gammas, and its parts come in a fixed order worth learning. First a lead collimator, a block drilled with long parallel channels, which admits only photons travelling nearly straight up them and absorbs the rest. Then a scintillator crystal, usually sodium iodide, which turns each surviving gamma into a flash of light.
Behind that sit photomultiplier tubes, which convert the flash to an electrical pulse and amplify it enormously. Position circuits then work out, from the relative sizes of the pulses, where on the crystal the flash happened.
In one line: the collimator selects photon direction, the scintillator converts each photon to light, and the photomultiplier tubes produce the electrical signals used to locate the emission.
Describe the drawing
A tracer site inside a patient outline emitting gammas in several directions towards a camera above: only the gamma travelling straight up the collimator channels reaches the crystal, the oblique ones are absorbed by the slats. The crystal turns that gamma into a flash of light, and the row of photomultipliers above it works out where the flash came from by comparing how bright each one sees it.
The collimator is where the image quality is decided, and the decision is a trade. Gammas leave the tracer in every direction, and the collimator's job is to keep only the ones whose direction still says something, those travelling straight up a channel, so that each flash in the crystal sits directly above the atom that decayed. That discipline is bought by throwing almost all of the emitted photons away, which is why a gamma scan takes minutes rather than the instant of an X-ray exposure.
Longer, narrower channels sharpen the image and discard more photons; shorter, wider ones collect faster and blur. The same trade as the intensifying screen of the X-ray lesson, run in the opposite direction.
The image is less detailed than a CT slice, and that is acceptable. A tracer shows where the activity is, not what the anatomy looks like, so hospitals routinely overlay the two kinds of scan, taking structure from one and function from the other.
PET: annihilation as a beacon has moved to the next part of this lesson.
When the dose is the point has moved to the next part of this lesson.
ASSESSMENT FOCUS
- A tracer answer needs both halves of the choice. Radiation that escapes the body to be detected, and a half-life matched to the procedure. Name technetium-99m and its six hours wherever an example is asked for, and indium-111 and its 2.8 days when the study runs over days, as labelled white cells hunting an infection do.
- Half-life questions must separate the two mechanisms before combining them. Physical is decay, biological is excretion, and the effective half-life comes from 1/TE = 1/TP + 1/TB. Check the answer is smaller than both inputs, because that is the one thing the arithmetic guarantees.
- Give the gamma camera's parts in beam order, as the photon meets them. Lead collimator passing only the gammas travelling straight up its channels, scintillator crystal turning each survivor into a flash of light, photomultiplier tubes converting the flash to a pulse, and position circuits placing it on the map.
- Function against structure is the comparison. Tracers image what tissue is doing, while X-ray and CT image what it looks like.
CHECK YOURSELF
Technetium-99m, physical half-life 6.0 hours, is bound to a compound the body clears with a biological half-life of 8.0 hours. Calculate the effective half-life of the dose, and explain why an alpha emitter with the same half-life would be useless with a gamma camera.
Show a hint
Add the rates, never the half-lives; then ask what actually reaches the detector.
Show the answer
1/TE = 1/6.0 + 1/8.0 = 0.292 h−1, so TE = 3.4 hours, shorter than either input, as the reciprocal sum guarantees.
Averaging the two half-lives would give 7.0 hours, which is wrong, because it is the fractional rates of loss that add, not the times.
An alpha emitter is stopped within a fraction of a millimetre of tissue, so almost none of its radiation reaches an external detector. The whole dose is deposited in the patient and no image is formed.
A tracer maps function, not shape, and the half-life that matters is the effective one: 1/T_E = 1/T_P + 1/T_B.
Photons have to be what leaves the patient, so a gamma camera takes a gamma emitter.
The camera reads in beam order: the collimator selects photon direction, the scintillator converts each photon to light, and the photomultipliers produce the signals that locate it.
WORKBOOK
Printable practice for this topic: original exam-style questions with room to work, and a fully worked answer book. Free to use; please do not redistribute or sell.
Or read them with their mark schemes on the radionuclide imaging and the gamma camera questions page.
WHERE TO GO NEXT
- Exponentials and logarithms is the maths this lesson leans on, worked through step by step.
CHECK YOUR PROGRESS
Rate how confident you feel with each objective for this lesson. Ratings are saved in this browser, on this device, unless you sign in.
- Explain what a medical tracer is, and why its half-life and emission type must be chosen carefully.
- Distinguish physical, biological and effective half-life, and combine them with 1/T_E = 1/T_P + 1/T_B.
- Describe how emitted gamma rays are used to build an image of where the tracer went.
Open the full revision checklist to track your progress across the whole unit.